Evaluating Gastrojejunostomy Techniques in Pancreatoduodenectomy: Side-to-Side vs End-to-Side Approaches and Impact on Delayed Gastric Emptying
Highlight
- The IPAD trial compared side-to-side versus end-to-side gastrojejunostomy in pancreatoduodenectomy (PD) for impact on delayed gastric emptying (DGE).
- No statistically significant difference was observed in the incidence of DGE between the two surgical reconstruction techniques.
- Postoperative complication rates, nutritional outcomes, and 90-day quality of life were similar between groups, indicating both techniques are equivalent.
- The study provides robust randomized controlled trial evidence, challenging previous retrospective suggestions favoring side-to-side anastomosis to reduce DGE.
Study Background
Pancreatoduodenectomy (PD) remains a complex surgical intervention primarily performed for malignant or benign conditions of the pancreatic head, distal bile duct, or periampullary region. Despite refinements in technique and perioperative care, delayed gastric emptying (DGE) remains a prevalent and challenging postoperative complication, affecting up to 40% of patients following PD. DGE can impair oral intake, extend hospital stays, increase healthcare costs, and negatively impact postoperative quality of life (QoL). Consequently, various surgical strategies have been investigated to reduce its incidence.
Reconstruction of the alimentary tract after PD can be achieved by different gastrojejunostomy configurations, predominantly side-to-side (SSGJ) and end-to-side (ESGJ). Retrospective studies have suggested that side-to-side anastomosis might facilitate more efficient gastric emptying, hypothetically by preserving gastric motility and reducing anastomotic tension. However, until now, high-quality randomized controlled trial (RCT) evidence directly comparing these two approaches has been lacking, raising uncertainty over the optimal reconstruction to mitigate DGE.
Study Design
The IPAD study was designed as a prospective, randomized, open-label controlled trial conducted in two high-volume pancreatic surgery centers in France. Eligibility criteria included adult patients undergoing PD for benign or malignant pathologies. Patients were randomized intraoperatively in a 1:1 allocation to receive either a side-to-side gastrojejunostomy (SSGJ) or an end-to-side gastrojejunostomy (ESGJ) as the definitive method of gastrointestinal reconstruction.
The primary endpoint was the incidence of delayed gastric emptying, defined according to International Study Group of Pancreatic Surgery (ISGPS) criteria, over a 90-day postoperative follow-up period. Secondary endpoints included rates of other postoperative complications such as pancreatic fistula and biliary fistula, need for reintervention, mortality, nutritional status parameters, and patient-reported quality of life assessed by the validated GastroIntestinal Quality of Life Index (GIQLI).
Key Findings
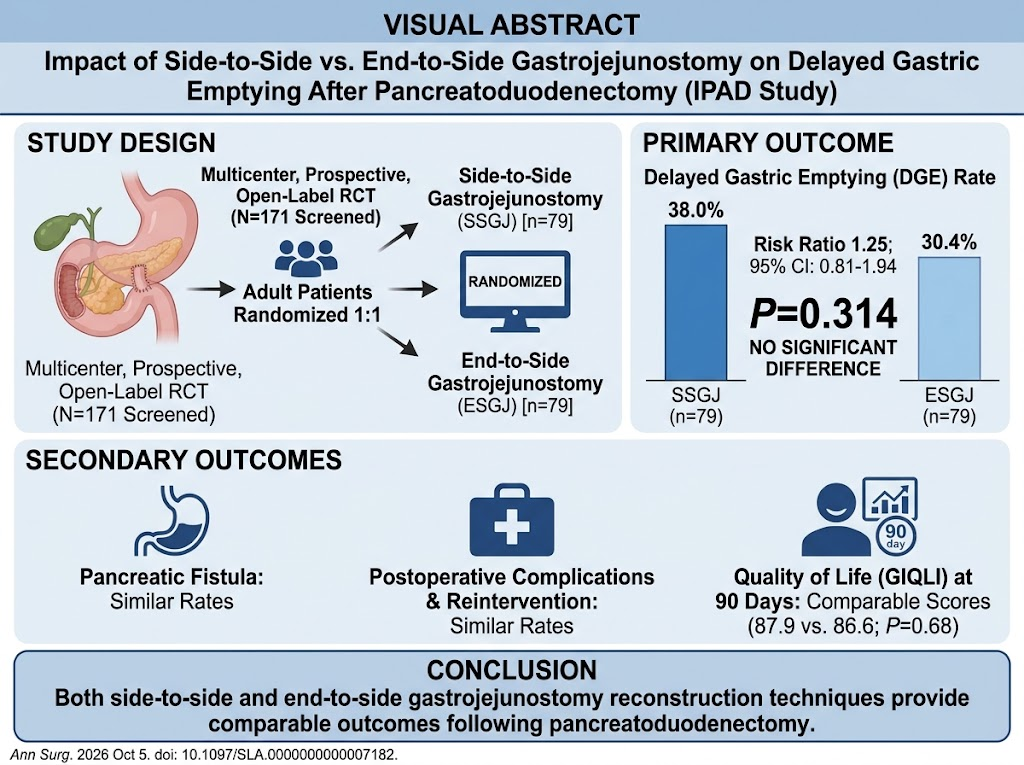
Between May 1, 2021, and July 1, 2023, of 171 patients screened, 158 were randomized equally to the two surgical techniques (79 patients each). Baseline demographics and clinical characteristics were largely comparable, though there were some differences in sex distribution, hypertension prevalence, and rates of chronic obstructive pulmonary disease. These factors were accounted for in analyses.
The incidence of DGE was 38.0% in the SSGJ group versus 30.4% in the ESGJ group. The risk ratio was 1.25 with a 95% confidence interval of 0.81 to 1.94, and the difference was not statistically significant (P=0.314). Secondary outcomes showed comparable rates of clinically relevant postoperative pancreatic fistula, biliary fistula, rates of surgical reintervention, and mortality between groups.
At 90 days, there was no significant difference in nutritional parameters, including serum albumin and body weight, between the groups. Patient-reported quality of life, measured by GIQLI, was similar with scores of 87.9 for SSGJ and 86.6 for ESGJ (P=0.68), indicating comparable functional recovery and well-being.
Statistical and Clinical Interpretation
The trial’s findings impart a clear message that the type of gastrojejunostomy configuration—side-to-side versus end-to-side—does not significantly impact delayed gastric emptying rates in the PD setting. Confidence intervals exclude large effect sizes favoring either technique, reinforcing the conclusion of equivalency for these clinically relevant outcomes. Additionally, similar postoperative complication rates and quality of life further support the interchangeable utility of either surgical method.
Expert Commentary
The IPAD randomized controlled trial fills an important evidence gap regarding reconstruction techniques after PD, a procedure with considerable postoperative morbidity. Prior retrospective studies were limited by potential confounding and bias, and the IPAD study provides level 1 evidence showing that the surgical choice between side-to-side and end-to-side gastrojejunostomy does not significantly alter the risk of DGE or meaningful clinical outcomes.
While the mechanisms underlying DGE are multifactorial—involving denervation, inflammation, and motility disruption—this study suggests that mechanical configuration of the gastrojejunostomy alone is not a dominant determinant.
Limitations include the open-label design, although the objective nature of endpoints like DGE reduces bias risk. The study was conducted in specialized centers, which may limit generalizability to lower-volume settings. Future research might explore adjunctive approaches such as pharmacologic prokinetics or neuromodulation to further mitigate DGE risk.
Conclusion
The IPAD randomized trial provides rigorous evidence that side-to-side and end-to-side gastrojejunostomy reconstructions after pancreatoduodenectomy are comparable in terms of delayed gastric emptying rates, postoperative complications, nutritional outcomes, and quality of life. Surgeons may select the anastomotic technique based on their experience, institutional preferences, or intraoperative considerations without concern for significant differences in these outcomes. This trial informs surgical decision-making and supports personalized approaches to gastrointestinal reconstruction after PD.
Funding and ClinicalTrials.gov Registration
The study was performed at two high-volume pancreatic centers in France. Specific funding details were not provided in the abstract. Future publications may provide comprehensive disclosures.
References
- Robin F, Wasielewski E, Chaouch MA, et al. Impact of Side-to-Side Versus End-to-Side Gastrojejunostomy on the Rate of Delayed Gastric Emptying After Pancreatoduodenectomy (IPAD study): A Randomized Controlled Trial. Ann Surg. 2026 Oct 5. PMID: 42832388.
- International Study Group of Pancreatic Surgery (ISGPS). Delayed gastric emptying (DGE) after pancreatic surgery: definition and grading. Surgery. 2007.
- Winter JM, Cameron JL. Pancreatoduodenectomy: Therapy for pancreatic and periampullary malignancies. Surg Oncol Clin N Am. 2012.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.