Enhancing Inter-Visit Care in Internal Medicine Residency: Integrating Structural Support and Educational Curriculum
Highlight
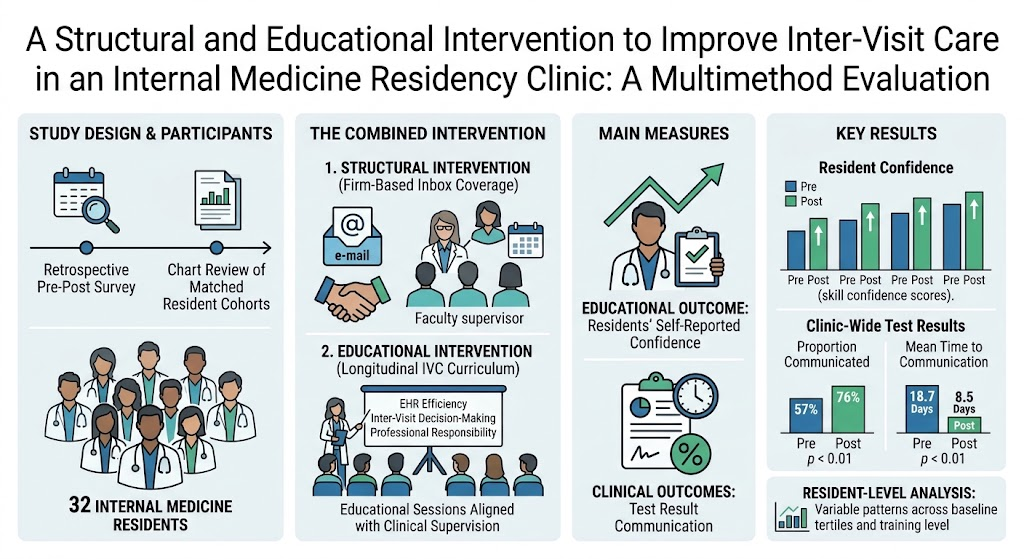
This study demonstrates that a combined firm-based inbox coverage system and a longitudinal educational curriculum significantly improves internal medicine residents’ confidence and proficiency in managing inter-visit care tasks, including timely test result communication.
The intervention reduced the mean time to communicate test results from 18.7 days to 8.5 days and increased communication rates from 57% to 76% at the clinic level.
Study Background
Inter-visit care (IVC)—encompassing tasks such as management of test results, asynchronous patient communications, and clinical decision-making between scheduled visits—represents an expanding and clinically significant aspect of outpatient practice. Despite its critical role in patient safety, diagnostic follow-up, and care continuity, IVC remains variably taught and inconsistently supervised in many residency programs.
Previous interventions have targeted either the educational or structural aspects of IVC independently, but the lack of an integrated approach may overlook important synergies between clinical systems and learning processes. This gap poses a risk of suboptimal patient care and inadequate preparation of residents for managing evolving ambulatory care demands. Addressing this unmet need, Birnbaum et al. implemented and evaluated a combined educational and structural intervention to enhance IVC management in an academic internal medicine residency continuity clinic.
Study Design
This multimethod evaluation included 32 internal medicine residents at an academic continuity clinic during the 2023-2024 academic year. The intervention comprised two components: (1) a firm-based inbox coverage system ensuring continuity of test result follow-up with shared faculty supervision and dedicated inbox office hours; and (2) a longitudinal curriculum focused on electronic health record (EHR) efficiency, clinical reasoning in inter-visit decision-making, and reinforcement of residents’ professional responsibilities in IVC.
Educational sessions were closely aligned with clinical supervision mechanisms to foster integrated learning and practice improvements. The evaluation employed a retrospective pre-post survey assessing residents’ self-reported confidence in IVC-related skills and a chart review comparing pre-intervention and post-intervention data on test result communication rates and timeliness.
Key Findings
Educational Outcomes: Residents reported significantly increased confidence across multiple IVC skill domains following the curricular implementation. These domains included navigating the EHR efficiently, clinical reasoning for inter-visit decisions, and understanding professional accountability in patient communication.
Clinical Outcomes: At the clinic level, the proportion of test results communicated to patients rose markedly from 57% before the intervention to 76% after implementation (p<0.01). In parallel, the average time to communicate test results decreased substantially from 18.7 days to 8.5 days (p<0.01), indicating improved timeliness and possibly heightened patient safety.
Resident-Level Analysis: When stratified by baseline communication tertiles and training level, resident performance showed variable patterns of improvement, suggesting that individual and experiential factors influence uptake and execution of IVC practices. Senior residents demonstrated relatively greater gains, consistent with progressive responsibility during training.
Expert Commentary
This study underscores the complex, multidimensional nature of inter-visit care, which requires not only discrete skills but also effective system-level supports and supervision. The alignment of education with a structured firm-based inbox system reflects best practices in residency training that emphasize both knowledge acquisition and real-world application under supervision.
Limitations include the single-center design and patient population, which may limit generalizability. Additionally, reliance on self-reported confidence may introduce subjective bias, although this was bolstered by objective clinical metrics. Further research could explore sustainability and scalability of such integrated interventions across various ambulatory care settings.
Conclusion
Birnbaum and colleagues provide compelling evidence that integrated curricular and structural interventions can significantly enhance both education and clinical outcomes related to inter-visit care in internal medicine residency clinics. By improving residents’ confidence and efficiency in managing asynchronous patient communications and test result follow-up, such programs can potentially elevate ambulatory patient safety and continuity of care.
This approach highlights the necessity of treating inter-visit care as a critical and teachable competency within graduate medical education, supported by faculty supervision and aligned clinical systems. Future directions may include incorporation into accreditation standards and broader dissemination to optimize ambulatory care quality.
Funding and ClinicalTrials.gov
Not applicable.
References
1. Birnbaum JF, Urquidi J, Chen B, Bravo R, Gandhi PB, Swails JL. A Structural and Educational Intervention to Improve Inter-Visit Care in an Internal Medicine Residency Clinic: A Multimethod Evaluation. Journal of General Internal Medicine. 2026 Sep 3. PMID: 42693370.
2. Singh H, et al. Managing Test Results in Ambulatory Care: The Impact of Electronic Alerts. Journal of General Internal Medicine. 2010;25(10):1097-1103.
3. Ogrinc G, et al. Teaching and Assessing Physicians’ Knowledge, Skills, and Attitudes Regarding Patient Safety and Systems Improvement: A Guide for Health Professions Education. Joint Commission Resources; 2010.
4. Groves PS, Kearney MH. Sustaining Continuity in Residency Clinics: The Role of Team-Based Oversight. Academic Medicine. 2018;93(2):198-204.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.