Highlight
– Thyroid radiofrequency ablation (RFA) demonstrates a 29% lower mean one-year healthcare cost compared to hemithyroidectomy in the evaluated Canadian tertiary centers.
– Cost savings with RFA primarily originate from obviating operating room and inpatient hospitalization expenses.
– Repeat RFA treatments and delayed surgeries due to nodule regrowth significantly impact the overall cost-effectiveness.
– Deterministic sensitivity analyses identify thresholds where RFA and hemithyroidectomy costs converge, emphasizing patient selection and procedural volume significance.
Study Background
Thyroid nodules are commonly encountered in clinical practice, with some requiring intervention due to size, symptomatology, or suspicion for malignancy. Traditionally, hemithyroidectomy remains the standard surgical intervention offering definitive treatment. However, it entails operative risks, prolonged recovery periods, and substantial healthcare resource utilization.
Radiofrequency ablation (RFA) has emerged as a minimally invasive alternative, especially for benign nodules. It offers advantages such as outpatient management, less morbidity, and rapid recovery. Despite its clinical promise, comprehensive health economic evaluations quantifying system-level cost implications of RFA compared to classical surgery have been limited. This evidence gap is critical as the adoption of RFA expands globally, necessitating cost analyses from the perspective of publicly funded healthcare systems to guide rational allocation of scarce resources.
Study Design
The study employed a retrospective micro-costing methodology spanning January 2023 to May 2025, analyzing 112 hemithyroidectomies and 42 thyroid RFA procedures performed at two tertiary care centers in Toronto, Canada. Micro-costing involves granular accounting of each cost component incurred throughout the entire patient care episode.
The patient care cycle considered extended from initial consultation through one-year post-procedure follow-up, capturing outpatient visits, procedure-related expenses, consumables, professional fees, pathology services, hospital stays, and ancillary diagnostics. Costs were reported in 2025 Canadian Dollars using a bottom-up approach, reflecting the perspective of a single-payer publicly funded healthcare environment.
Both outpatient and inpatient hemithyroidectomy cases were included; RFA cases were primarily outpatient. Deterministic one-way sensitivity analyses evaluated the impact of variables such as the proportion of patients needing repeat RFA, delayed hemithyroidectomy after initial ablation, and procedural volume on costs and cost equivalence thresholds.
Key Findings
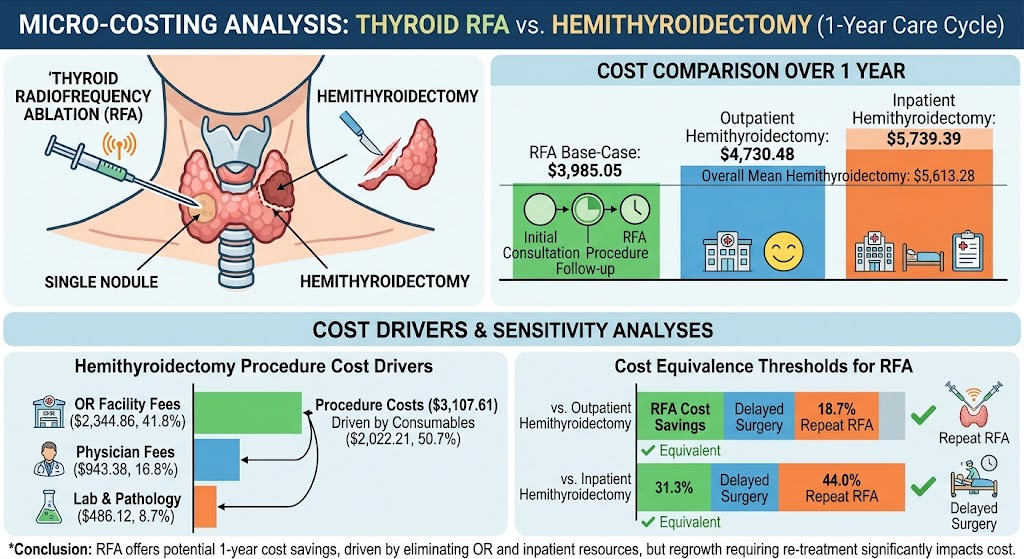
The micro-costing analysis revealed that the base-case average total cost for one year of thyroid RFA was $3985.05 per patient. The bulk of this cost (78.0%) derived from the RFA procedure itself, with consumables and supplies accounting for over half of the procedure cost ($2022.21 or 50.7%).
By contrast, hemithyroidectomy incurred a mean cost of $5613.28 per patient over one year, with outpatient cases averaging $4730.48 and inpatient cases $5739.39. Key cost drivers for hemithyroidectomy were the operating room facility fees (41.8% of procedure costs), followed by physicians’ fees for surgeons and anesthesiologists (16.8%), and laboratory/pathology services (8.7%).
Consequently, thyroid RFA delivered a 29.0% (approximately $1628.23) cost reduction compared to the mean hemithyroidectomy cost. This economic advantage stems predominantly from eliminating operating room utilization and associated inpatient admissions, underlining RFA’s outpatient feasibility and resource efficiency.
Sensitivity analyses underscored critical factors influencing cost parity:
– Cost equivalence between RFA and outpatient hemithyroidectomy was reached if 13.3% of patients undergoing RFA subsequently required delayed surgery, or if 18.7% underwent repeat RFA.
– For inpatient hemithyroidectomy comparisons, equivalence thresholds were higher—31.3% delayed surgery or 44.0% repeat RFA.
These data emphasize that while RFA is economically attractive, patient selection impacting rates of nodule regrowth and retreatment drives overall cost-effectiveness. Repeat ablative procedures and surgeries due to incomplete ablation or recurrence diminish cost savings.
Expert Commentary
Thyroid RFA represents a paradigm shift in thyroid nodule management toward less invasive, outpatient modalities. This study rigorously quantifies the cost implications within a single-payer system, confirming previously hypothesized economic benefits.
While RFA offers meaningful cost reductions, the analysis highlights vulnerabilities linked to nodule regrowth necessitating additional interventions. Current clinical guidelines advocate strict criteria for RFA candidacy—benign, well-characterized nodules, and careful volumetric assessment. Thus, optimal patient selection and adherence to standardized ablation protocols are vital to maximize both clinical outcomes and economic advantages.
Limitations include retrospective design, regional cost structure specific to Canadian healthcare which may limit direct generalizability, and absence of detailed quality-of-life or functional outcome assessments complements to cost data. Future prospective studies integrating cost-effectiveness with patient-centered outcomes, and longer-term follow-up could inform reimbursement policies and guideline incorporation.
In summary, RFA serves as an effective, less resource-intensive alternative to hemithyroidectomy for select patients. Its implementation should be coupled with institutional expertise and longitudinal monitoring to ensure durable clinical success and sustainable healthcare expenditure.
Conclusion
The micro-costing analysis demonstrates that thyroid RFA is a cost-saving alternative to hemithyroidectomy over a one-year care cycle within a publicly funded Canadian healthcare context. Cost benefits derive from avoidance of operating room and inpatient admission expenses. However, the rate of repeat ablative treatments and delayed surgical interventions critically modulate overall cost-effectiveness.
Maximizing RFA’s benefits necessitates rigorous patient selection, standardized procedural techniques, and integration of health economic considerations into clinical decision-making. As RFA adoption expands, continuous evaluation of cost and clinical outcomes will be essential to optimize resource allocation and enhance patient care in thyroid nodule management.
Funding and ClinicalTrials.gov
The study does not report specific funding sources. No clinical trial registration information is provided.
References
1. Gao H, Forner D, Levy BB, Kamalraj P, Puri R, Higgins KM, Philteos J, Eskander A. Micro-Costing Analysis of Thyroid Radiofrequency Ablation Compared with Hemithyroidectomy in Outpatient and Inpatient Settings. Thyroid. 2026 Aug;36(9):951-960. PMID: 42541345.
2. Pacella CM, Mauri G, Vitti P, et al. Minimally invasive treatment of thyroid nodules: recommendations for clinical practice. Endocrine. 2019 Jan;63(1):176-187.
3. Korean Society of Thyroid Radiology. 2021 Clinical Practice Guideline for Radiofrequency Ablation of Benign Thyroid Nodules. Ultrasonography. 2021;40(2):137-164.
4. Trimboli P, Dobrinja C, Cappelli C, et al. Radiofrequency ablation for thyroid nodules: the state of the art. J Endocrinol Invest. 2022;45(3):425-433.
5. Chammas MC, De Menezes MI, Burhan AM. Economic evaluation of thyroid nodule management: a cost-benefit analysis. Eur J Endocrinol. 2020;182(5):515-523.