Highlight
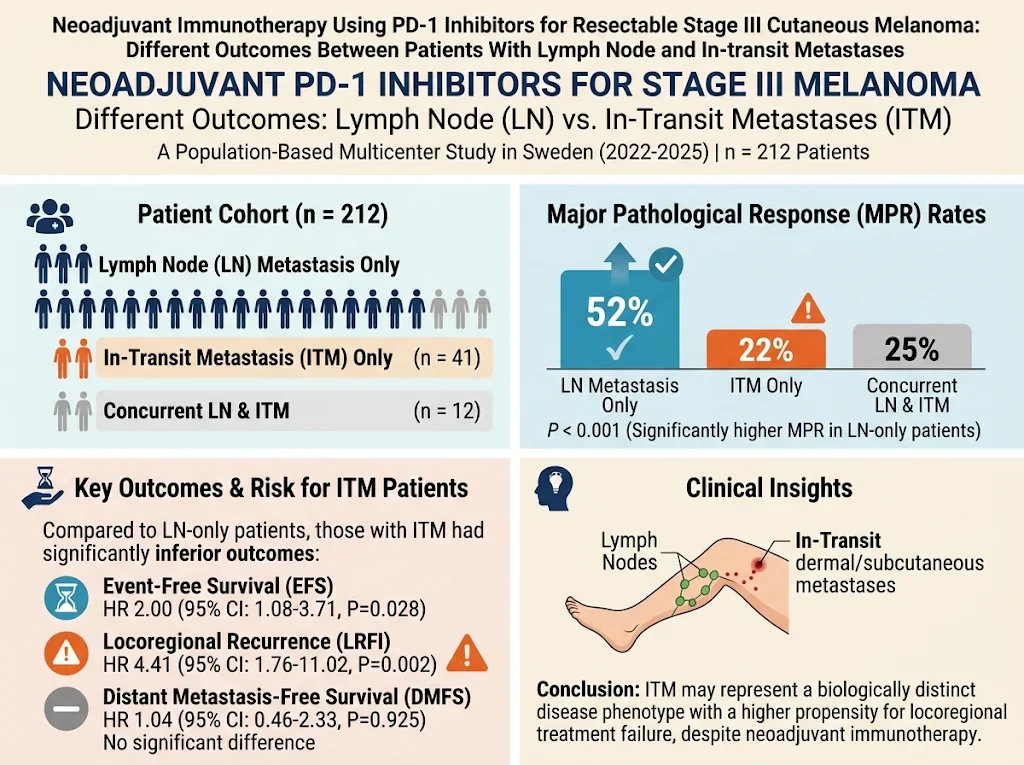
This comprehensive real-world study investigates neoadjuvant PD-1 inhibitor immunotherapy in resectable stage III cutaneous melanoma, comparing patients with lymph node (LN) metastases and those with in-transit metastases (ITM). Key findings include a significantly higher major pathological response (MPR) rate in LN metastases, worse event-free survival (EFS), and higher locoregional recurrence in ITM, suggesting a distinct biological behavior of ITM.
Study Background
Cutaneous melanoma is a highly aggressive skin cancer that, at stage III, often manifests with regional lymph node involvement and less commonly with in-transit metastases (ITM), defined as metastases in lymphatic vessels between the primary tumor site and regional lymph nodes. Neoadjuvant immunotherapy using programmed death-1 (PD-1) inhibitors has become a preferred treatment for patients with resectable stage III melanoma, aiming to enhance systemic anti-tumor immunity and reduce recurrence risk.
Despite increasing adoption, real-world data remain sparse, particularly concerning patients with ITM, a subgroup hypothesized to have distinct tumor biology and clinical outcomes. This study sought to clarify the efficacy and safety of neoadjuvant PD-1 blockade among stage III melanoma patients with different metastatic patterns in a population-based cohort.
Study Design
This observational multicenter cohort study enrolled 212 patients with macroscopic stage III cutaneous melanoma treated with neoadjuvant PD-1 inhibitors from 2022 to 2025 across five academic Swedish cancer centers. Patients were stratified into three groups based on metastatic presentation at diagnosis: LN metastasis only (the most common), ITM only, and concurrent LN and ITM involvement.
The primary endpoint was major pathological response (MPR), defined as a robust tumor regression on pathological review after therapy. Secondary endpoints included event-free survival (EFS), locoregional recurrence-free interval (LRFI), distant metastasis-free survival (DMFS), and safety outcomes. Median follow-up was approximately 15 months.
Key Findings
The study found a marked difference in pathological response rates among the groups. Patients with LN metastases alone showed the highest MPR rate (52%), compared with 22% in ITM only and 25% in those with concurrent LN and ITM disease (P < 0.001), indicating significantly poorer tumor regression in ITM cases.
Survival analyses revealed that patients with ITM experienced inferior outcomes in terms of EFS and LRFI compared to LN-only patients. Multivariable Cox regression confirmed ITM as an independent risk factor for worse EFS (hazard ratio [HR] 2.00; 95% confidence interval [CI] 1.08–3.71; P = 0.028) and substantially increased risk of locoregional recurrence (HR 4.41; 95% CI 1.76–11.02; P = 0.002).
Interestingly, unadjusted analyses initially suggested differences in distant metastasis-free survival. However, after adjusting for confounders, no significant association between ITM and DMFS was observed (HR 1.04; 95% CI 0.46–2.33; P = 0.925), implying that systemic metastatic risk may be similar between groups.
Safety profiles were consistent across cohorts, with no unexpected adverse events related to neoadjuvant PD-1 inhibitors reported.
Expert Commentary
This study is the largest cohort specifically addressing the outcomes of ITM patients undergoing neoadjuvant PD-1 immunotherapy, providing valuable real-world evidence that ITM represents a biologically distinct disease phenotype within stage III melanoma. The lower MPR and worse EFS highlight that standard PD-1 blockade may be less effective in locoregional disease control where ITM is present.
Mechanistically, ITM may reside in unique tumor microenvironments with distinct immunosuppressive factors or altered lymphatic biology, mediating differential response to checkpoint inhibitors. The high locoregional recurrence risk supports consideration of intensified local therapies or combined systemic strategies targeting ITM.
Limitations include the observational design and relatively short median follow-up, which may underestimate late recurrences or survival differences. Additionally, heterogeneity in concurrent treatments and lack of biomarker stratification merit consideration. Nevertheless, results align with evolving concepts that melanoma subtypes require tailored therapeutic approaches based on metastatic pattern and biology.
Current guidelines for resectable stage III melanoma emphasize neoadjuvant immunotherapy but do not differentiate ITM from LN disease specifically. This study underscores the need to reevaluate treatment algorithms and potentially incorporate multimodal management strategies for patients with ITM.
Conclusion
In summary, neoadjuvant PD-1 inhibitor therapy achieves higher pathological response rates and better event-free survival in patients with stage III melanoma presenting with lymph node metastases compared to those with in-transit metastases. ITM portends a higher risk of locoregional recurrence, likely reflecting a distinct tumor biology and therapeutic challenge.
These findings advocate for further research into specialized treatment approaches for ITM, including adjunctive local therapies, combination immunotherapy regimens, or novel agents targeting the tumor microenvironment. For clinicians, incorporating metastatic pattern into treatment planning and patient counseling is critical for optimizing outcomes in stage III melanoma.
Funding and Clinical Trials
The study was supported by academic cancer centers across Sweden. Specific funding details were not provided. Clinical trial registration information is not applicable as this was an observational study.
References
1. Krabbe E, et al. Neoadjuvant Immunotherapy Using PD-1 Inhibitors for Resectable Stage III Cutaneous Melanoma – Different Outcomes Between Patients With Lymph Node and In-transit Metastases. Ann Surg. 2026;284(5):950-956. PMID: 42522061.
2. Gershenwald JE, et al. Melanoma staging: Evidence and evolving concepts. Clin Dermatol. 2016;34(5):524-535.
3. Long GV, et al. Neoadjuvant checkpoint blockade for melanoma—rationales and current trials. Nat Rev Clin Oncol. 2021;18(9):527–542.
4. Grob JJ, et al. Immune checkpoint inhibitors in melanoma: patient selection and management. Dermatol Ther. 2017;7(4):529-545.
5. Eggermont AMM, et al. Adjuvant pembrolizumab versus placebo in resected stage III melanoma. N Engl J Med. 2018;378(19):1789-1801.