Highlight
Both morphea and systemic sclerosis (SSc) are associated with increased overall cancer incidence compared to the general population.
Distinct cancer profiles observed: morphea patients showed increased female reproductive and breast cancers; SSc patients had elevated lung and hematologic malignancies.
Young patients exhibited the highest relative cancer risk, underscoring the need for vigilant surveillance.
Immunosuppressant therapy was linked to a reduced cancer risk in both morphea and SSc cohorts.
Study Background
Systemic sclerosis (SSc) is a well-established autoimmune connective tissue disease characterized by fibrosis, vasculopathy, and immune dysregulation. Prior studies have documented an increased risk of malignancy, particularly hematologic and lung cancers, in patients with SSc. By contrast, morphea, a localized scleroderma variant affecting the skin without systemic involvement, lacks robust population-level data regarding cancer risk. The uncertain and conflicting evidence regarding cancer incidence in morphea limits informed clinical decision-making. Given the potential shared fibrotic and immune-mediated pathogenic mechanisms between morphea and SSc, elucidating their cancer risk profiles is critical for guiding surveillance and management.
Study Design
This retrospective, population-based cohort study leveraged linked administrative health databases from Quebec, Canada, covering the period from 1996 to 2019, with cancer follow-up through December 31, 2020. The cohorts included 6181 patients with morphea and 8133 with SSc, identified based on validated diagnostic algorithms requiring at least two specialist billing claims or hospitalizations at least two months apart using relevant ICD-9 and ICD-10 coding. Cancer incidence was ascertained through linkage to the provincial cancer registry.
The primary outcomes were overall and site-specific incident cancers, for which standardized incidence ratios (SIRs) were calculated against the general population, using Canadian Cancer Registry rates. Cumulative cancer incidence was estimated using Fine-Gray competing risk models accounting for death as a competing event. Multivariable Cox regression analyses adjusted for potential confounders evaluated factors associated with incident cancer, including immunosuppressant use.
Key Findings
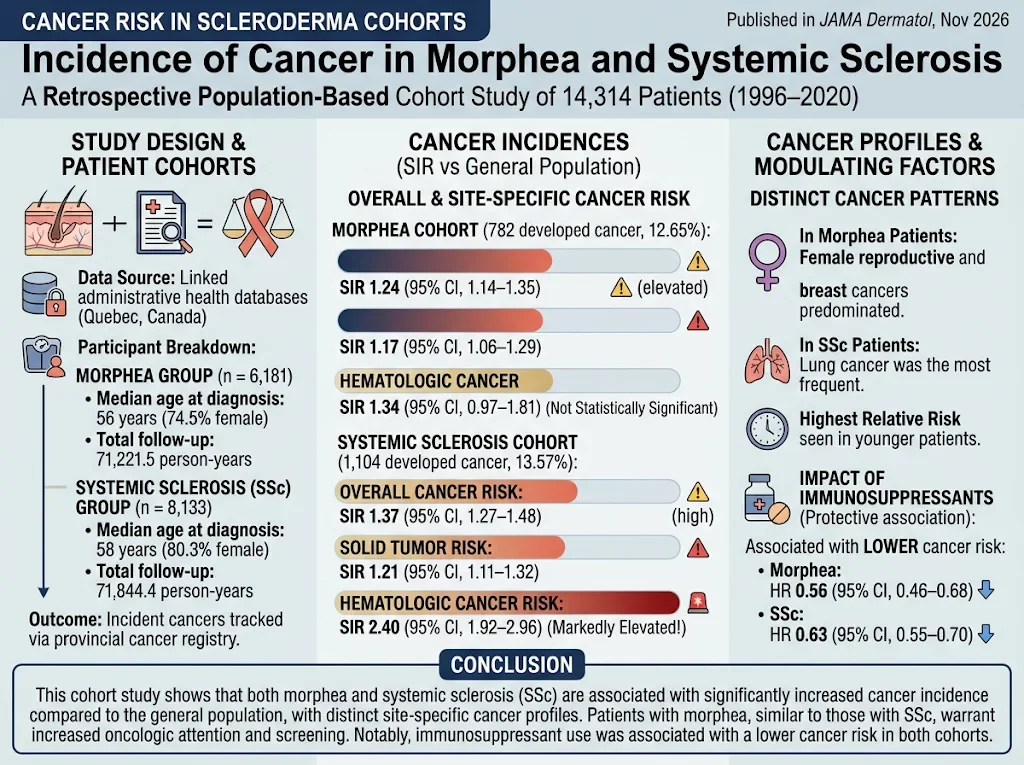
During follow-up encompassing approximately 71,221 person-years for morphea patients and 71,844 person-years for SSc patients, 12.65% of morphea patients and 13.57% of SSc patients developed cancer.
Increased Overall Cancer Incidence
Both morphea and SSc cohorts demonstrated statistically significant increases in overall cancer incidence compared to the general population: morphea SIR 1.24 (95% CI, 1.14–1.35) and SSc SIR 1.37 (95% CI, 1.27–1.48).
Solid Tumor Risk
Elevations in solid tumor risk were observed in both cohorts: morphea SIR 1.17 (95% CI, 1.06–1.29) and SSc SIR 1.21 (95% CI, 1.11–1.32). Notably, cancer type distributions differed across groups.
Hematologic Malignancies
Hematologic cancer risk was markedly elevated in the SSc cohort (SIR 2.40; 95% CI, 1.92–2.96) but did not reach statistical significance for morphea (SIR 1.34; 95% CI, 0.97–1.81).
Site-Specific Cancer Patterns
Breast and female reproductive cancers predominated in the morphea group, while lung cancer was the most frequent malignancy in the SSc cohort. These differences may reflect disease-specific pathogenesis or exposures.
Effect of Age and Immunosuppressant Use
Younger patients demonstrated the highest relative cancer risk in both autoimmune groups. Interestingly, immunosuppressant therapy was associated with a significantly lower hazard of incident cancer: hazard ratio (HR) 0.56 (95% CI, 0.46–0.68) in morphea and HR 0.63 (95% CI, 0.55–0.70) in SSc, suggesting a complex interplay between immune modulation and oncogenesis.
Expert Commentary
This study substantially advances understanding of cancer risk in morphea, positioning it alongside systemic sclerosis as a condition with increased oncologic vigilance warranted. The distinct cancer profiles underscore the importance of individualized risk assessment rather than a uniform screening approach. The increased hematologic malignancy risk in SSc aligns with prior reports and may be linked to chronic immune activation, fibrosis, and occult paraneoplastic phenomena.
The protective association of immunosuppressants challenges previous assumptions that immune suppressive therapies may increase cancer risk and instead suggests that controlling aberrant immune activity might reduce malignant transformation risk. However, confounding by indication and other biases must be considered.
Limitations include reliance on administrative coding, potential misclassification, and lack of granular clinical data (e.g., autoantibody status, disease subtype, smoking). Additionally, the retrospective design precludes causal inference.
Conclusion
This large population-based analysis confirms that both morphea and systemic sclerosis confer an elevated incidence of cancer relative to the general population, albeit with divergent tumor profiles. These findings highlight morphea patients as an under-recognized group requiring oncologic awareness. Future prospective studies should evaluate the benefit of specific cancer screening strategies tailored by autoimmune phenotype and explore mechanistic pathways underlying the distinct malignancy risks. Optimizing immunosuppressive regimens may offer dual benefits of disease control and cancer risk mitigation.
Funding and Clinical Trials
This study was supported by institutional research grants and provincial health research funding agencies in Quebec, Canada. No relevant clinical trial registration was noted.
References
1. Muha J, Joly-Chevrier M, Nedjar H, Julien F, Aw K, Muntyanu A, Ghazal S, Hundal S, Osman M, Dorais M, Rahme E, Kaouache M, Netchiporouk E. Incidence of Cancer in Morphea and Systemic Sclerosis. JAMA Dermatol. 2026 Nov 11. doi: 10.1001/jamadermatol.2026.4685. Epub ahead of print. PMID: 43013302.
2. Tansley SL, Ng WF. Cancer in systemic sclerosis. Rheumatology (Oxford). 2016;55(1):5-14.
3. Shah AA, Rosen LB, Hummers LK, et al. Utility of Cancer Screening in Systemic Sclerosis. Arthritis Care Res (Hoboken). 2020;72(2):304-312.
4. Wu M, Assassi S. Malignancy in Systemic Sclerosis: Risk Factors, Screening, and Clinical Implications. Curr Rheumatol Rep. 2017;19(11):66.
5. Miller FW, Lamb JA, Schmidt J, Nagaraju K. Risk Factors and Etiopathogenesis of Systemic Sclerosis-Associated Malignancy. Rheumatology (Oxford). 2020;59(Suppl 4):iv35-iv43.