Highlight
– Refractory primary autoimmune hypophysitis (PAH) affects 22% of PAH patients, characterized by glucocorticoid (GC) resistance or GC dependency.
– GC-dependent refractory PAH shows clinical distinctions: higher serum prolactin, larger pituitary stalk, and increased hypogonadotropic hypogonadism.
– Pregnancy-associated hypophysitis is less prevalent in refractory, GC-dependent cases.
– Combination immunosuppressive treatments like mycophenolate mofetil and rituximab achieve radiological control.
– Glucocorticoid-related metabolic side effects are common, emphasizing need for alternative therapies.
Study Background
Primary autoimmune hypophysitis (PAH) is an inflammatory disorder of the pituitary gland resulting in pituitary insufficiency and mass effects. The first-line treatment standard is glucocorticoid (GC) therapy, which typically reduces inflammation and alleviates symptoms. However, treatment failure, characterized by persistent or recurrent hypophysitis symptoms during or after GC therapy, remains a significant clinical challenge. Defining the refractory form of PAH, including GC resistance and GC dependency, has been elusive, complicating management and prognostication. Furthermore, there is an unmet need for structured diagnostic criteria and effective treatment pathways to guide clinicians managing these complex cases.
Study Design
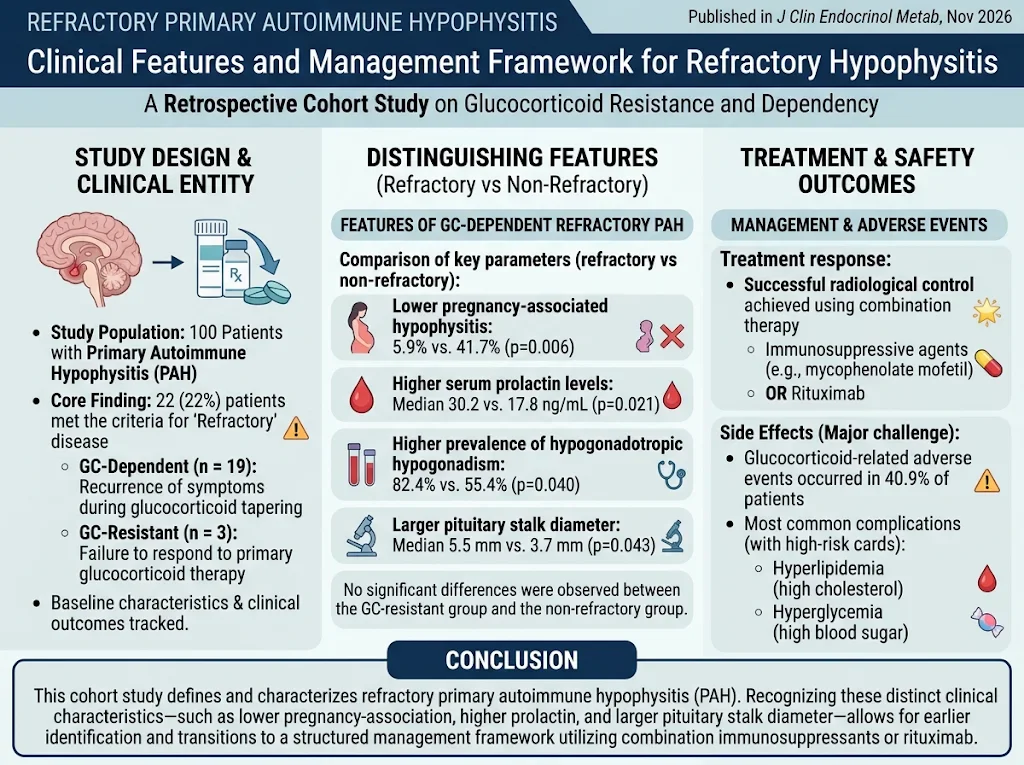
This was a retrospective cohort study involving 100 patients diagnosed with primary autoimmune hypophysitis. Refractory PAH was defined as either GC resistance (where disease activity did not improve with standard GC therapy) or GC dependence (where patients relapsed upon steroid tapering). Of these patients, 22 met the refractory criteria: 19 were GC-dependent and 3 GC-resistant. Initial clinical, biochemical, and radiological data were compared between refractory and non-refractory groups. An exploratory screening model for identifying refractory PAH was developed based on these findings. Treatment response was retrospectively evaluated, including the use of immunosuppressants and biologic therapies.
Key Findings
Refractory PAH accounted for 22% of the cohort, with the majority being GC-dependent. Distinct clinical features differentiated GC-dependent refractory patients from non-refractory ones:
Pregnancy-associated hypophysitis was significantly less frequent in the refractory group (5.9% vs. 41.7%; p=0.006).
Median serum prolactin levels were higher in refractory patients (30.2 ng/mL vs. 17.8 ng/mL; p=0.021), reflecting greater pituitary stalk involvement.
Hypogonadotropic hypogonadism was more prevalent in refractory cases (82.4% vs. 55.4%; p=0.040), indicating more extensive anterior pituitary dysfunction.
The median pituitary stalk diameter was enlarged in refractory patients (5.5 mm vs. 3.7 mm; p=0.043), consistent with more severe inflammation.
The GC-resistant group (n=3) did not show significant differences from the non-refractory group, suggesting limited statistical power due to small numbers.
Management of refractory PAH included addition of immunosuppressive agents such as mycophenolate mofetil and rituximab, which were effective in achieving radiological and clinical control of disease activity. However, GC therapy was associated with adverse events in 40.9% of patients, predominantly metabolic effects such as hyperlipidemia and hyperglycemia, underscoring the need for alternative or adjunctive treatments.
Expert Commentary
This study represents an important advancement in understanding refractory PAH by establishing clear clinical and biochemical criteria. The observed distinct phenotype of GC-dependent refractory hypophysitis, including markers such as elevated prolactin and pituitary stalk enlargement, provide mechanistic and practical insights. The rarity of GC-resistant cases suggests that treatment resistance is more commonly encountered as steroid dependency with relapse on tapering.
Importantly, the favorable response to immunosuppressants and rituximab aligns with the autoimmune pathogenesis of PAH and supports their use in refractory cases. These findings may inform future prospective studies and consensus guidelines. Limitations include retrospective design, small resistant subgroup size, and lack of standardized imaging protocols. External validation of the screening model and management framework will be essential.
Conclusion
The study delineates refractory primary autoimmune hypophysitis as a distinct clinical entity marked by glucocorticoid dependence or resistance. GC-dependent refractory disease features characteristic clinical and radiological parameters, facilitating early identification. Immunosuppressive combination therapies show promise for controlling disease and minimizing glucocorticoid toxicity. The authors’ proposed screening and treatment pathway offers a clinically valuable approach to managing this complex condition, addressing a critical unmet need in endocrinology practice. Further multicenter prospective studies are warranted to refine management algorithms and optimize patient outcomes.
Reference
Zhai X, Xu Z, Xu T, Zhang Y, Duan L, Wang L, Yao Y, Xing B, Deng K, Feng F, Liang Z, You H, Yang H, Pan H, Zhu H. Clinical Features and Management Framework for Refractory Hypophysitis: A Cohort Study. J Clin Endocrinol Metab. 2026 Nov 12:dgag434. doi: 10.1210/clinem/dgag434. Epub ahead of print. PMID: 43017889.