Chronic Steroid Use Does Not Increase Short-Term Risks After Distal Pancreatectomy: Insights from a Large National Database
Highlight
- Chronic glucocorticoid use is not independently associated with increased short-term complications following distal pancreatectomy.
- The rate of pancreatic fistula, major and minor complications, mortality, readmission, and prolonged hospital stay are similar between steroid-dependent and non-steroid groups after surgery.
- Propensity score matching confirms comparable postoperative outcomes despite chronic immunosuppressive therapy.
- This evidence suggests chronic steroid dependence should not be an absolute contraindication to distal pancreatectomy, although further research on dosage effects is warranted.
Study Background
Distal pancreatectomy is a common surgical procedure for lesions involving the body and tail of the pancreas. It carries a typical risk profile including pancreatic fistula, infection, and other perioperative complications. Patients on chronic glucocorticoids, commonly prescribed for autoimmune, inflammatory, or other chronic conditions, are traditionally considered to have elevated surgical risk due to immunosuppression, impaired wound healing, and metabolic effects. However, robust contemporary data assessing the true impact of chronic steroid use on outcomes after pancreatic resections are scarce. This knowledge gap poses a clinical dilemma in balancing surgical benefit with perceived risk for this vulnerable population.
Study Design
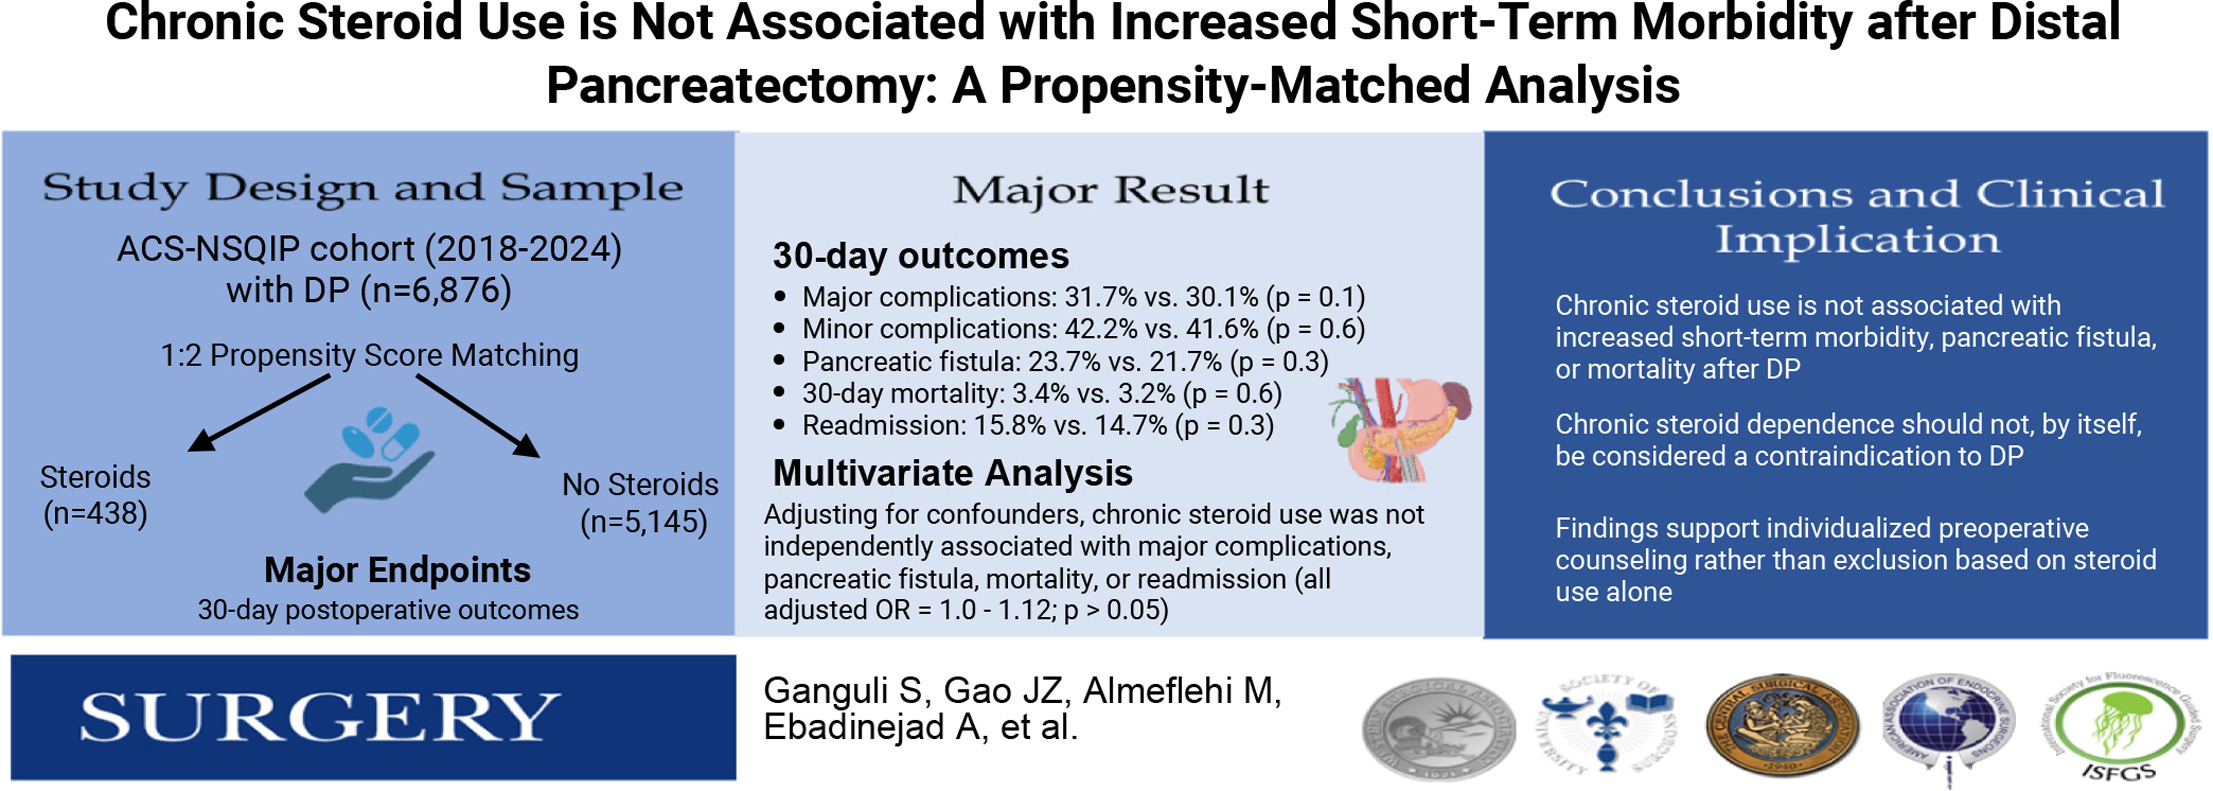
This retrospective cohort study utilized the National Surgical Quality Improvement Program (NSQIP) database from 2018 to 2024, encompassing 6,876 patients who underwent distal pancreatectomy. Chronic steroid use was defined according to NSQIP criteria, capturing patients receiving systemic glucocorticoids for prolonged periods. To minimize confounding, researchers applied propensity score matching at a 1:2 ratio comparing 438 steroid-dependent patients with 876 matched controls not on steroids. Primary endpoints included 30-day postoperative complications (major and minor), pancreatic fistula incidence, all-cause mortality, hospital readmissions, and length of stay.
Key Findings
The study found no statistically significant differences between steroid and non-steroid groups in the incidence of pancreatic fistula (23.7% vs 21.7%, P=0.3), major complications (31.7% vs 30.1%, P=0.1), minor complications (42.2% vs 41.6%, P=0.6), mortality (3.4% vs 3.2%, P=0.6), readmission rates (15.8% vs 14.7%, P=0.3), or prolonged hospital stay (11.4% vs 10.5%, P=0.5). Multivariate logistic regression adjusting for demographic and clinical covariates confirmed that chronic steroid use was not independently associated with adverse short-term outcomes. The balanced baseline characteristics after matching strengthen the internal validity of these results.
Expert Commentary
These findings counter prevailing clinical assumptions that chronic steroids invariably elevate perioperative risk. The absence of a significant effect on complications including pancreatic fistula—a major morbidity determinant—suggests that physiological adaptations or steroid dosing may modulate surgical vulnerability more than previously appreciated. Nonetheless, limitations exist. NSQIP does not capture exact steroid dosage, duration, or indications, limiting dose-response analysis. Residual confounding from unmeasured variables, such as nutritional status or disease severity, cannot be excluded. Additionally, longer-term outcomes beyond 30 days were not assessed. Future prospective studies stratifying steroid regimens and exploring biological mechanisms of perioperative risk modulation would enhance personalized surgical risk assessment.
Current clinical guidelines do not categorically recommend against pancreatic surgery in steroid-dependent patients but emphasize careful perioperative management including stress-dose steroids and infection prophylaxis. This large-scale, propensity-matched analysis provides evidence to support these recommendations and may reassure surgeons considering distal pancreatectomy for this cohort.
Conclusion
In summary, chronic glucocorticoid use does not appear to increase short-term morbidity or mortality following distal pancreatectomy. These data suggest that steroid dependence should not be deemed an absolute contraindication to this surgery when clinically indicated. Surgeons should continue individualized risk-benefit evaluations but may consider chronic steroid therapy less of a limiting factor than previously thought. The study underscores the value of rigorous propensity-matched analyses in informing surgical decision-making for high-risk populations. Further research assessing steroid dose, timing, and long-term post-pancreatectomy outcomes is warranted to enhance perioperative care for patients on chronic immunosuppressive therapy.
Funding and Clinical Trials
The study did not report specific funding sources. Given its retrospective design based on a national database, no registered clinical trial number was applicable.
References
1. Ganguli S, Gao JZ, Almeflehi MF, Ebadinejad A, Aziz H. Chronic steroid use is not associated with increased short-term morbidity after distal pancreatectomy: A propensity-matched analysis. Surgery. 2026 Sep 3:110606. PMID: 42791100.
2. Postlewait LM, Ethun CG, Leiting JL, et al. Perioperative glucocorticoid use in patients undergoing pancreatic surgery: a review. J Surg Oncol. 2019;120(8):1353-1361.
3. Raevsky E, Gorbatov L, Nagarajan K, et al. Impact of chronic corticosteroid use on postoperative outcomes after surgery: a systematic review. Ann Surg. 2020;271(2):365-372.
4. National Surgical Quality Improvement Program (NSQIP) Participant Use Data File. American College of Surgeons, 2018-2024.
5. Meneses-Echavez JF, Garcia-Hermoso A, et al. Effect of corticosteroids on wound healing in surgery: a systematic review and meta-analysis. Wound Repair Regen. 2023;31(1):10-21.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.